
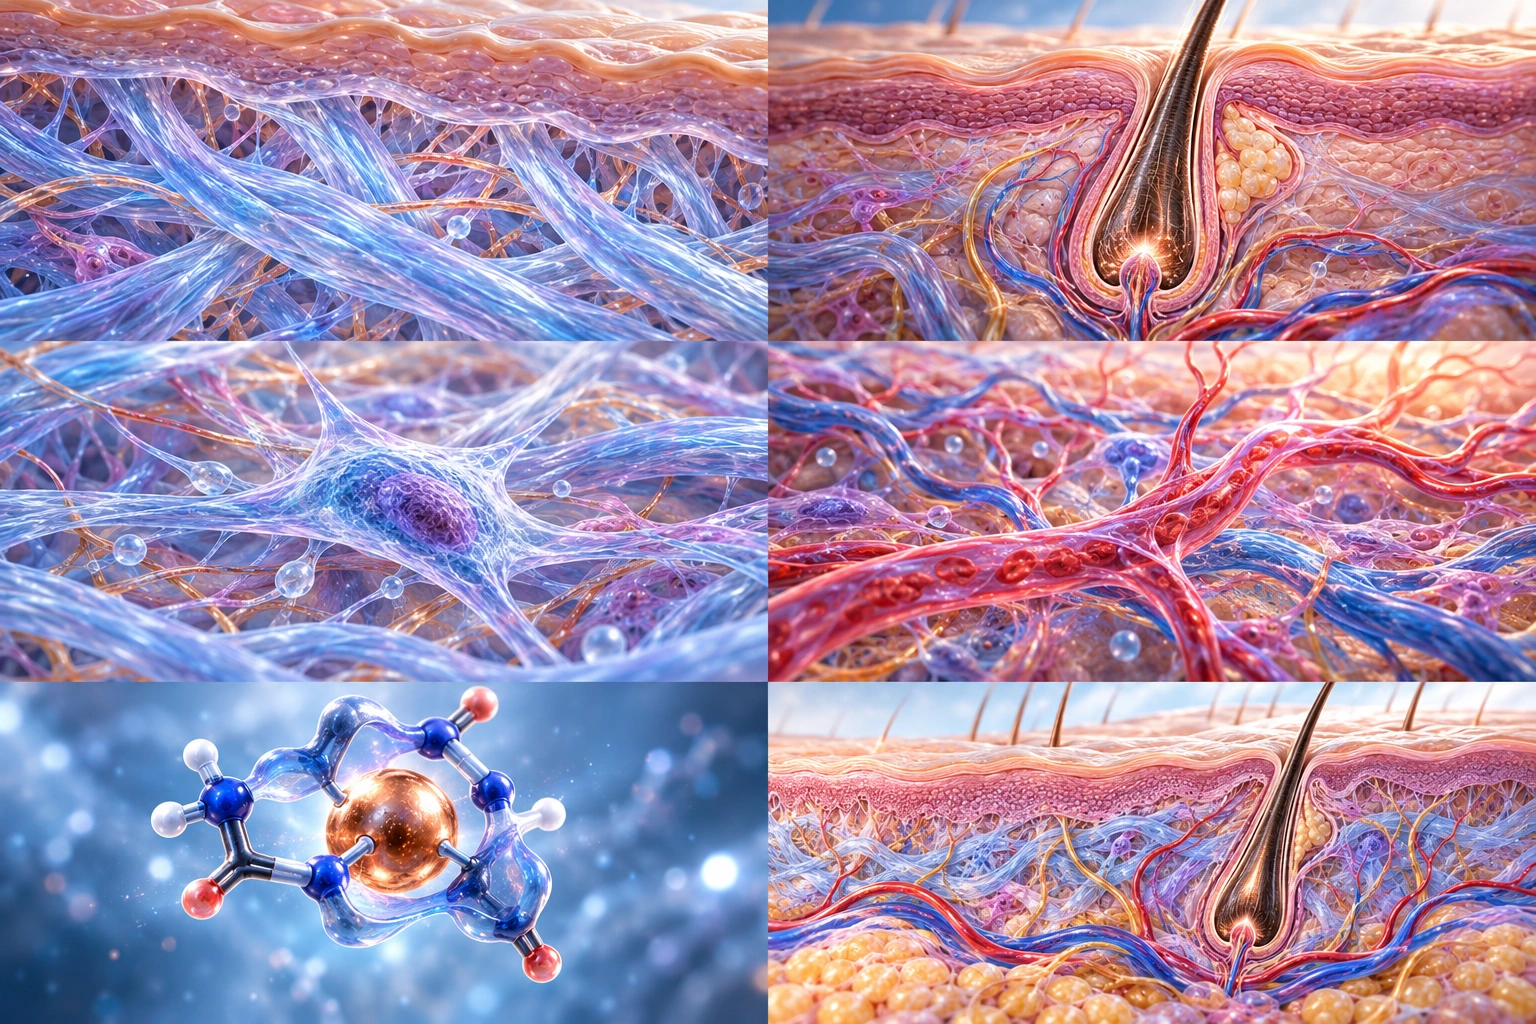
Skin repair
Skin repair is one of the longest-standing reasons for interest in GHK-Cu, including how damaged or ageing skin recovers and renews itself.
Explore the research →
A naturally occurring copper peptide with long-standing research interest around skin quality, collagen, hair and tissue repair.
GHK-Cu is best known as a copper peptide associated with skin renewal, collagen, hair and tissue repair. The attraction is easy to understand: these processes are closely tied to how skin looks and heals, how its structure is maintained and, potentially, how the scalp and hair respond as we age.
Skin repair is one of the longest-standing reasons for interest in GHK-Cu, including how damaged or ageing skin recovers and renews itself.
Explore the research →GHK-Cu is frequently associated with collagen and the supporting structure that helps give skin its firmness and resilience.
Explore the research →Cosmetic interest centres on smoother texture, firmness and the visible changes associated with sun exposure and ageing.
Explore the research →GHK-Cu also appears in discussions and products aimed at supporting the scalp and encouraging healthier-looking hair.
Explore the research →GHK is made from three amino acids: glycine, histidine and lysine. Parts of this short peptide coordinate a copper ion, forming the complex called GHK-Cu. Think of the peptide as a small molecular holder, rather than copper floating freely.
That binding changes how copper participates in local chemistry. Researchers study the complex in collagen, tissue remodelling and skin repair; it is not a proven delivery service that automatically carries copper wherever the body needs it.
See the studies & trials →Copper binding is established chemistry; outcomes depend on the product and route.
Read a primary source ↗These are the tissues and biological systems behind the interest in GHK-Cu.
Skin repair is one of the longest-standing reasons for interest in GHK-Cu, including how damaged or ageing skin recovers and renews itself.
Laboratory, animal and some human topical studies have explored wound repair, skin appearance and the rebuilding of supporting skin tissue.
Mixed preclinical & human evidenceExplore the studies →GHK-Cu is frequently associated with collagen and the supporting structure that helps give skin its firmness and resilience.
Laboratory studies suggest effects on genes and repair processes involved in collagen and the surrounding tissue structure.
Mechanistic & preclinical evidenceExplore the studies →Cosmetic interest centres on smoother texture, firmness and the visible changes associated with sun exposure and ageing.
Some small human studies and product-specific data are encouraging, although the evidence is not strong enough to support every anti-ageing claim made for copper peptides.
Limited human evidenceExplore the studies →GHK-Cu also appears in discussions and products aimed at supporting the scalp and encouraging healthier-looking hair.
There are plausible biological reasons for the interest, but strong clinical evidence for meaningful hair regrowth is still limited.
Early / limited evidenceExplore the studies →Patients undergoing circumoral CO2 laser skin resurfacing
Normal human fibroblasts in culture
Published topical GHK / GHK-Cu research
This score reflects completed human outcome evidence. A registered or recruiting trial does not count until results are reported.
These are editorial evidence-depth ratings on a 1–5 scale, not a statistical result or a single scientific formula. They summarise how much relevant evidence is present in each separate category and how mature that evidence is.
Research themes are shown separately from the strength of the human evidence so biological interest is not confused with proven clinical benefit.
GHK-Cu attracts interest because skin quality, collagen, wound repair and hair health form a coherent story. The most credible practical evidence is topical and product-specific; injectable routines are much less characterised.
Explore the everyday goalsWhat the desired change means in daily life, and what makes an experience useful to understand.
Fine lines, uneven texture and a less resilient-looking complexion drive skincare interest. People want a visible cosmetic improvement, often as part of an existing routine rather than as a stand-alone intervention.
People losing weight may become interested in skin quality or a looser-looking appearance. The hoped-for change is a better-looking skin surface; preventing or reversing substantial loose skin is a much larger claim.
Hair and scalp interest centres on shedding, thinner areas and a fuller appearance. A convincing account needs to distinguish new growth from styling, reduced breakage or concurrent hair treatments.
The tissue-remodelling story also attracts interest in irritated or damaged skin. Cosmetic appearance, wound healing and injected use are different questions with different evidence requirements.
Selected first-hand accounts illustrate the goals and the variation in experience. They are examples, not a representative sample or proof of an effect.
A first-hand report connects interest in skin appearance during weight loss with an unexpected perceived hair change. It is an uncontrolled observation.
Read the discussionA skincare discussion illustrates the desire for cosmetic change and uncertainty about injected GHK-Cu. A question about benefit is not proof of benefit.
Read the discussionOpen an area to distinguish human findings from laboratory explanations.
Small topical and post-procedure studies provide limited human support, but formulations and outcomes vary.
Cell research links GHK-Cu with extracellular-matrix, collagen and repair-related signalling.
What this means: Promising for topical skin research, but broad anti-ageing claims remain ahead of the evidence.
Human evidence is mainly product- and procedure-specific rather than a general healing treatment programme.
Laboratory work supports effects on fibroblasts, matrix biology and repair signalling.
What this means: Biologically credible, with limited direct clinical proof for most everyday uses.
Robust controlled evidence for meaningful hair regrowth is limited.
Copper-peptide and follicle biology offer a rationale, but do not establish a predictable result.
What this means: An active area of interest rather than an established hair-loss treatment.
See the amount, how often it was used and how long each study ran. Published human research and community descriptions each carry their own source label, so you can see where the numbers came from.
Human topical skin-care research does not establish this injectable pattern. Monday to Friday gives the calendar copy five days each week; those particular weekdays are an editable choice.
Five days per week · amount each time
Five days per week · amount each time
Five days per week · amount each time
Human research is mainly topical and product-specific; there is no validated general injectable GHK-Cu dosing protocol in the evidence set.
Patients after circumoral CO2 laser resurfacing
This was a published human study. It involved Patients after circumoral CO2 laser resurfacing. Route: Applied to the skin. The study lasted post-treatment recovery period. The figures below describe the research design, not a personal schedule.
| First amount studied | Product-specific topical regimen |
|---|---|
| How often? | As used in the post-procedure skin-care protocol |
| How was it given? | Applied to the skin |
| How long? | Post-treatment recovery period |
Start / initial: Product-specific topical regimen
End / target: Product-specific topical regimen
Frequency: As used in the post-procedure skin-care protocol
Route: Topical
Study duration: Post-treatment recovery period
Source: PMID 16847171 ↗
Product-specific research protocol; not a general dosing recommendation.
Topical use is usually discussed by product strength and directions. Injectable discussions often begin around 1 mg per day, but no human dose-finding study validates that starting amount.
Four-to-eight-week topical or injected courses are commonly described. Formulation, route and absorbed exposure are not interchangeable.
Intermittent topical use is widely discussed; there is no validated injectable maintenance dose, cycle or break interval.
Topical use is much more commonly supported and discussed. Injectable subcutaneous use also appears in peptide communities but is less established.
When injectable use is discussed, routine subcutaneous sites are more typical than targeted injection into skin, scalp or injured tissue. Evidence for a local injection advantage is lacking.
No consistent injection timing pattern has strong support; community discussion tends to focus more on repeated exposure than a particular time of day.
Multi-week courses are discussed, but injectable GHK-Cu lacks a validated human dosing framework for cosmetic or repair uses.
Much of the stronger human interest in GHK-Cu relates to topical or local skin products. Injectable community use should not be assumed to share the same evidence base.
Community reports describe what people say they do; they are not instructions, validated protocols, or evidence that a particular injection site or timing improves outcomes.Calculation example only. The amount below demonstrates the maths; it does not choose a dose or a preparation method.
The calculation uses the full concentration before rounding the display. U-100 markings measure volume; they are different from a medicine’s international units (IU). Different vial contents or liquid volumes require a new calculation.
Convert amounts, concentration, liquid volume and vial requirements. These tools do the arithmetic; they do not select a dose.
Purity, identity, quantity, sterility and endotoxin testing answer different questions. Learn how to read a COA and why a high purity percentage is not the same as confirming the amount in the vial.
A dose only makes sense alongside the population, route, frequency and duration. Start with where the number came from, then look at how it was delivered and how long the study actually ran.
Was it an authorised label, a human trial or a community-described pattern?
How was it given, and how often? The same number by a different route may not mean the same exposure.
Was this one dose, a short trial or long-term treatment? A study window is not automatically a recommended cycle.
Route means how a compound was delivered. It affects absorption and can completely change how a study should be interpreted.
An injection into the fatty layer just under the skin.
Common in peptide and metabolic-drug studies. It usually aims for systemic absorption rather than treating only the spot injected.An injection into muscle tissue.
Muscle can absorb a medicine differently from fat. An IM amount should not be assumed to be equivalent to a SubQ amount.Delivered directly into a vein.
This gives immediate bloodstream exposure and is commonly used in supervised research or clinical settings. It is not interchangeable with a home injection route.Delivered through the nose rather than by injection.
The amount delivered depends on formulation and device. A spray count alone does not tell you the dose unless concentration and spray volume are known.One thousand micrograms (mcg).
One thousandth of a milligram.
The amount is calculated for each kilogram of body weight.
A measure of biological activity used for some medicines; it cannot be converted to mg without compound-specific information.
For example SubQ, IM, IV, intranasal, oral or topical.
For example once daily, twice weekly or every seven days.
A protocol changes the amount over time rather than using one fixed amount throughout.
The time taken for the amount of a compound in the body to reduce by roughly half. It can influence study timing but does not by itself define a schedule.
Usually means an on-period followed by a stop or review. Many community 'cycles' have not been clinically validated.
A longer-term amount or interval used after an initial phase when a study or authorised treatment actually defines one.
Adding a specified liquid to a freeze-dried vial so a concentration can be calculated.
100 units equals 1 mL on a U-100 insulin syringe. The markings show volume, not peptide mass.
The summary above reflects the human or preclinical evidence currently represented on this profile.
Limited follow-up, small studies or absent controlled trials can leave uncommon and longer-term risks unresolved.
Route, product identity, quality and regulatory status can materially change the safety context; see the linked status sources below.
A worsening wound, spreading redness, fever or a severe skin reaction needs medical assessment rather than continued experimentation.
Follow the professional sources used across this profile, then see how the compound is currently described in regulatory and research terms.
Published human work is mainly topical and formulation-specific. It does not establish an authorised injectable GHK-Cu treatment schedule.
Topical clinical study · PubMed ↗Cosmetic serum, wound-care formulation and injectable product cannot be treated as equivalent exposures.
Topical evidence review · PubMed ↗Profile reviewed against its linked source record on 20 September 2026. See how evidence is assessed.
Save peptides, build plans, set reminders and keep track of your own supplies in a private My Explorer space.